
Platform in development · Pre-revenue

Kebeza PathEdge

Local capacity.
Shared expertise.

Scanner-agnostic pathology coordination for cytology and histology. Built around trained teams, existing equipment and accountable specialist review.

Founder-funded. Workflow validation and commercial economics are still to be established.

SPECIMEN → SPECIALIST
CYTOLOGY + HISTOLOGYDiagrammatic illustration
No patient data

The operating principle

Standardise the clinical workflow without forcing every laboratory to standardise its hardware.

Support the expertise already in the system. Make it easier to reach.

PathEdge’s development direction is a structured pathway from site submission to review, quality assurance and reporting. Acquisition R&D aims to reduce the work that depends on a scarce specialist standing beside the microscope.

Asynchronous review is the route to better throughput. Live remote microscopy has a focused role: adequacy checks, extra fields, focusing, escalation and teaching.

Explore the acquisition ladder

People make the pathway work

Screen locally where possible.
Review with responsibility.

Training is competency-based and supervised. A short course does not confer unrestricted independent practice or sign-out.

HIGHER-VOLUME CYTOLOGY SITES

On-site cytotechnologist

A cytotechnologist can screen Pap or FNAC material, select representative fields and prepare preliminary findings, with pathologist support and final review.

Refresher training and supervision strengthen this role. Cytotechnologists remain central to screening capacity.
PROPOSED LOWER-VOLUME MODEL

Local capture, pooled screening

Trained acquisition operators could support pooled remote cytotechnologists and pathologists, once broad, systematic capture is validated.

A few fields selected by an untrained operator cannot stand in for whole-slide screening.

  1. 01

    Submit

    Site information and suitable images, with a locked draft where appropriate.

  2. 02

    Review

    First pathologist interpretation and requests for additional information.

  3. 03

    Escalate

    Reasoned second opinion and senior review when needed.

  4. 04

    Sign out

    A qualified pathologist is responsible for the final report.

The workflow above describes the intended model under development, not a claim that every integration is live.

The acquisition ladder

Start with what is there.
Evaluate the next step.

Telepathology does not always mean whole-slide imaging. The specimen, clinical task and trained workforce determine which acquisition method is appropriate.

01

Existing whole-slide scanners

Use suitable WSI where available. Evaluate image quality, workflow fit and review requirements for the intended use.

Hardware-independent direction
02

Microscope-camera capture

Standardised selected fields can support appropriately screened material. An off-the-shelf camera is an acquisition option, not a scanner by itself.

Task-specific evaluation
03

Live remote microscopy

Use guided focusing and additional fields for adequacy, difficult areas, escalation or teaching.

Selected support needs
04

Manual whole-slide mosaics

Evaluate coverage, focus and assembly reliability before relying on systematic local capture for remote screening.

Evaluation planned
05

Affordable automated acquisition

Microscope retrofit and whole-slide acquisition R&D aimed at reducing dependence on specialist presence beside the microscope.

Research & development
06

AI assistance

Begin with acquisition quality, coverage, report preparation and documentation checks. Screening or decision support needs separate evidence and validation.

Future, separately validated

Pathology-wide by design

Different specimens.
Different acquisition demands.

Neither cytology nor histology can be reduced to a single universal capture method. Equipment and workflows must be evaluated for the task.

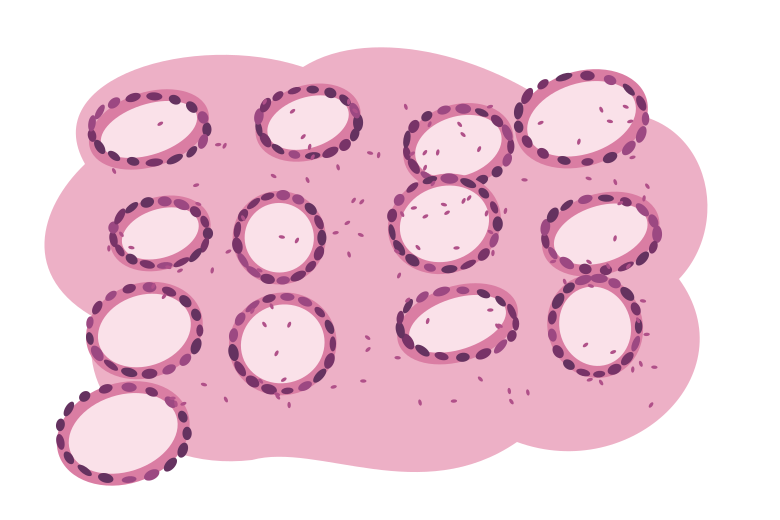
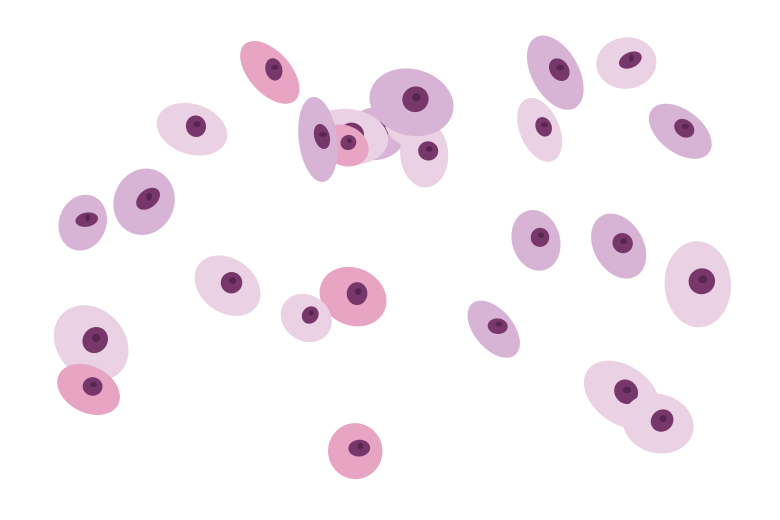
Diagrammatic cells showing separation and overlap

Cytology

Sparse abnormal cells, background clues, overlap and focal depth affect screening. Appropriate coverage and trained screening protect against the limits of selected fields.

Diagrammatic tissue architecture showing the importance of context

Histology

Full tissue context, dependable focus and colour matter. Extra levels, immunohistochemistry and other studies may still be needed for interpretation.

Diagrammatic illustrations. No diagnostic findings or patient images.

Targets to validate

Time matters.
So does getting it right.

These are pathway targets for suitable cases, subject to evaluation. They are not service guarantees or measured network-wide performance.

<3hours

Cytology

From sampling to report when same-day preparation and review are feasible.

1–3days

Routine histology

From tissue receipt at the laboratory, for suitable routine cases.

Same day

Diagnostic-ready H&E slides

For digital acquisition and remote sign-out once a suitable conventional slide already exists.

Extra levels, ancillary studies, immunohistochemistry, difficult consultations and inadequate samples require their own timelines.

Quality and evidence

Measure the complete case.

Proposed evaluation measures include completed cases per cytotechnologist-hour and pathologist-hour, site cost, turnaround and major discrepancy rate.

Historical regional cytology experience informs the work. It is distinct from independent diagnostic-accuracy validation and from cases processed by the current PathEdge software.

Clinical accountability stays with qualified professionals. Research use of records requires a valid legal basis, ethics and institutional review, permissions, access controls and appropriate agreements.

Explore the proposed evidence programme

A defined setting. A testable workflow.

What would PathEdge
need to do for your site?

Tell our office about your specimen types, staff and equipment. We can discuss the scope of an evaluation and the responsibilities it would require.

Already using PathEdge? Go to the existing-user sign-in.